


Algés, Oeiras Mon to Fri · 09:00 to 13:00 and 14:00 to 19:00 · Sat · 09:00 to 14:00
WhatsApp Book a consultation

Aesthetic gynaecology

Less intense orgasmsWhen the orgasm still happens, but comes weaker, shorter or less satisfying than before

“Less intense orgasms” describes what many women notice over a lifetime: orgasm is still there, but no longer has the strength, duration or pleasure of other phases. It is different from not being able to reach orgasm: here the response is maintained and what has changed is the intensity. It is a very common complaint and rarely has a single cause. Age and hormones, the pelvic floor, certain medications (such as some antidepressants), stress, tiredness, the relationship and the context of stimulation all play a part. Here we explain what may lie behind it, what is assessed and what helps, starting with what needs no technology, and what the clinic can offer, with honesty about what the evidence shows.

Reviewed by Dr Michelle Campagnoli, clinical director

  • 12recommendations from an international consensus for assessing and treating female orgasm problems
  • 1assessment consultation, always first
  • 70 €assessment booked through the website
Woman with braids and a rust-coloured sweater, eyes closed and wearing headphones, in a record shop

How to recognise it

Could it be less intense orgasms?

It is not a diagnosis: it is the perception that orgasm is no longer what it was. Since each woman experiences orgasm in her own way, what matters is the comparison with yourself, since when it changed and whether it bothers you.

Tick what you recognise0/7

Tick the signs you recognise in your case. This is not a diagnosis, it is only meant to give you an idea.

Do you have bleeding after the menopause or after sex, abnormal discharge, sudden or persistent pain during sex or in the intimate area, a changing lesion on the vulva, fever, blood in the urine, or persistent sadness that takes away your interest in everything? You need an assessment and should not wait. If you have suddenly lost sensation in the intimate area or in the legs, with loss of control of urine or stools, go to the emergency department or call 112. Out of hours, call SNS 24: 808 24 24 24.

Female doctor in a white coat showing a tablet with coloured circles to a grey-haired patient
Photograph of a consultation. The dots mark what the doctor assesses; the image does not show the intimate area.

Why it happens

What may lie behind less intense orgasms

Orgasm depends on several systems at the same time: hormones, circulation, nerves, muscles, brain and context. When one of them changes, the intensity can change. Choose a situation to see how it applies.

Age and hormones

With the fall in oestrogen, the intimate mucosa becomes thinner and drier, and the response to stimulation may take longer and be less marked. Perimenopause and the menopause can also bring less desire, poorer sleep and more tiredness. These changes are frequent, vary greatly from woman to woman and often have treatment.

What weighs on it

Accepting everything as “just a matter of age” and leaving dryness or pain untreated, which also take away involvement.

What helps

Assessing dryness and vaginal atrophy. Lubricants, moisturisers and low-dose vaginal oestrogen, prescribed by a doctor, may be part of the plan.

Normal or to be assessed

Normal variation or something to assess

The intensity of orgasm varies, and not all variation is a problem. What separates one from the other is a change that bothers you, how fast it came and what goes with it.

  • How it shows. The intensity changes from day to day or from phase to phase: weaker with tiredness, stress, haste or close to your period, stronger at other times.

  • When it happens. In busier or more demanding periods, after a poor night’s sleep, in a phase of change or as the years go by. Without pain or distress, it may be just a variation.

  • What the clinic does. The doctor listens to what is going on, reassures you when it is a usual variation and explains what tends to weigh in each phase.

  • At home. Sleeping, reducing haste, varying stimulation, using lubricant and talking to the person you share intimacy with.

Have you suddenly lost sensation in the intimate area or in the legs, with loss of control of urine or stools? Call 112 or go to the emergency department. If you have bleeding after the menopause or after sex, persistent pain, abnormal discharge or any doubts, out of hours you can call SNS 24: 808 24 24 24.

Book an assessment consultation

What can help

Options for less intense orgasms

The first line is not a technology. It is understanding what has changed and treating what is contributing: reviewing with the doctor any medication that may be an influence, treating dryness and pain with lubricants, moisturisers or, when indicated, low-dose vaginal oestrogen, pelvic floor physiotherapy, and sex therapy, individual or as a couple. In postmenopausal women with low desire that causes them distress, the use of testosterone is only discussed with the doctor and is not a treatment for orgasm itself. The treatment below is an additional option, assessed case by case and without promising results, with evidence that is still limited.

Book an assessment consultation
Dr Michelle Campagnoli, clinical director of Clínica Luxmed

First step

Assessment consultation

The doctor listens to what you are experiencing, examines your case and explains the suitable options. No treatment begins without this consultation.

May be considered when

you want to understand the cause and decide on the best path, with time and without commitment.

Book an assessment consultation
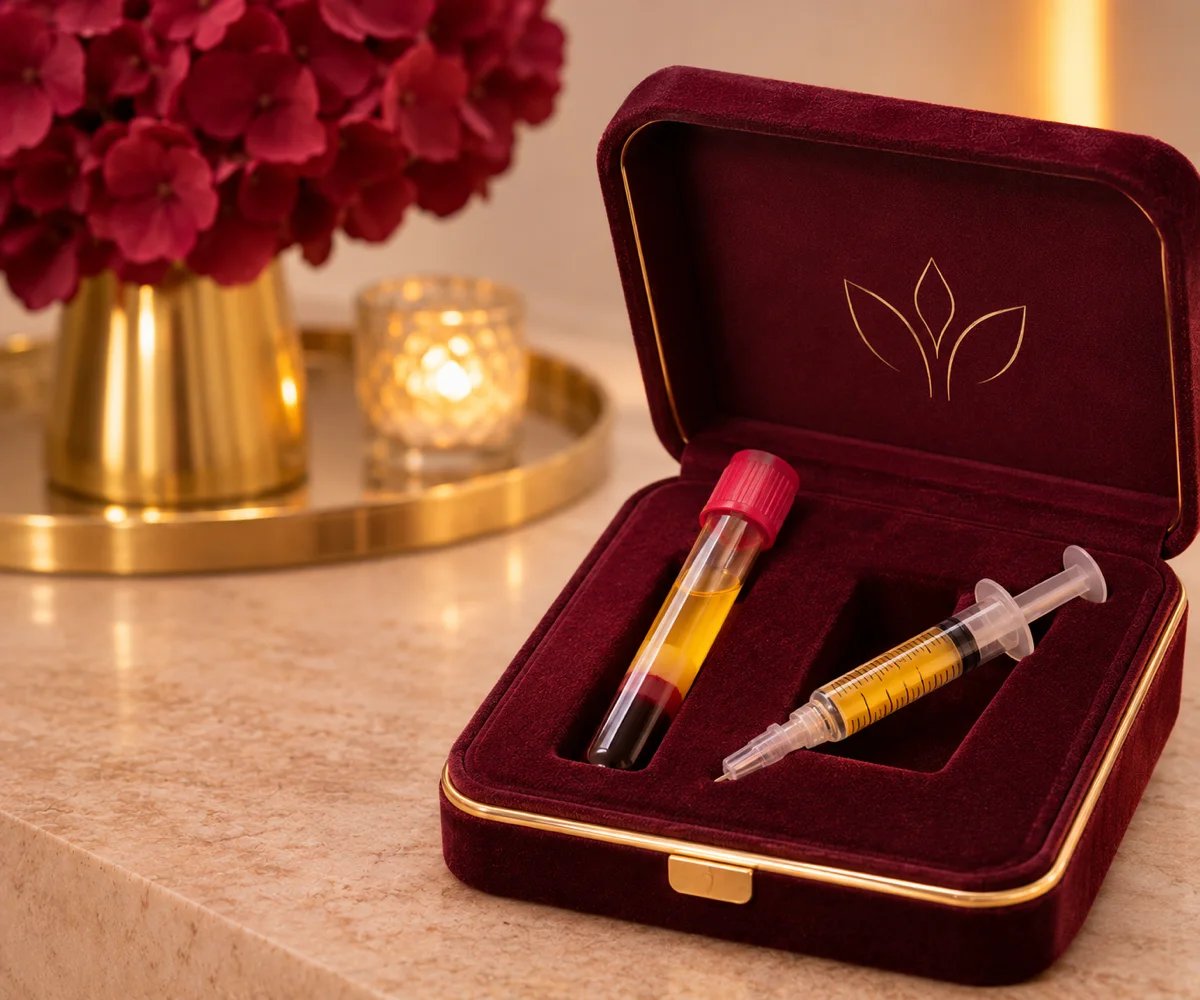
Plasma tube and syringe in a burgundy velvet case on a countertop

Injection

O-SHOT (Orgasm Shot)

Injection into the intimate area of platelet-rich plasma (PRP), obtained from a small sample of your own blood, with the aim of improving sexual response. The commercial name is not a promise: the studies are few and small, and the level of evidence is low. It does not replace assessment, medication review, physiotherapy or sex therapy.

May be considered when

the assessment has not found a cause that should be treated first (such as dryness, medication or pain), the first-line options have been done or considered, the doctor has explained what is known and what is not, and the decision is yours.

Find out more

What the journey looks like

From the first consultation to the plan tailored to you

No treatment begins without an assessment consultation with the doctor. Almost always the simplest and safest measures come first, and only then is more considered.

  1. 01At the clinic

    Assessment consultation

    The doctor listens to what has changed, when and in which situations, asks about medication, the menopause, births, surgeries and mood, and lets you speak in private and without rushing. She may suggest a simple questionnaire on sexual function.

  2. 02At the clinic

    Examination and assessment of the context

    When it makes sense, a gynaecological examination is carried out, the mucosa and lubrication are assessed, along with the state of the pelvic floor and whether there is pain, and treatable causes such as vaginal atrophy, an infection or a skin condition of the vulva are ruled out.

  3. 03At home and with other professionals

    Treating what weighs most

    Reviewing medication with whoever prescribes it, treating dryness or pain, starting pelvic physiotherapy when indicated and, if it helps, individual or couple sex therapy. In parallel, habits that matter, such as sleep and alcohol, are changed.

  4. 04Over time

    Reassessing and deciding

    What has changed and how you feel are assessed again. If the complaint persists nonetheless, the doctor explains the other routes, including the clinic’s additional options, with the evidence, the risks and the limits, and the decision is shared with you.

Day to day

What helps while you wait for the consultation

Simple, safe care, alongside the plan the doctor indicates.

It is not just you

Talking about this is the first step

Orgasm problems are among the sexual complaints most often reported by women, and yet many stay silent out of embarrassment or because they think it is “normal”. You do not need to have a “disease” to ask for help: if the change bothers you, it deserves to be assessed, and there is often something that can be done.

Saying what has changed, calmly

Putting a name to the change helps the doctor and helps whoever shares intimacy with you to understand what is going on.

In practice: note since when you noticed, in which situations and what changed in your life at that time, and take the notes to the consultation.

Giving time and varying stimulation

Arousal prepares the orgasm: with more time, more variety and less haste, it usually comes stronger.

In practice: try different rhythms, touches and moments, and say what you prefer. Knowing your own body also helps.

Using lubricant and treating dryness

Dryness and discomfort reduce arousal and involvement.

In practice: a water- or silicone-based lubricant during sex and a regular vaginal moisturiser. If that is not enough, talk at the consultation about vaginal oestrogen.

Looking after sleep, stress and the body

Tiredness and tension lower sexual response, and regular physical activity improves circulation and mood.

In practice: sleep as much as you need, set aside screen-free time as a couple and move regularly. If you do pelvic floor exercises, check that you are doing them correctly.

Dr Michelle Campagnoli, clinical director of Clínica Luxmed

Who will look after you

An assessment carried out by the doctor

At Luxmed, the first step is always an assessment consultation with Dr Michelle Campagnoli. She is the one who listens to what has changed, assesses the mucosa, the pelvic floor and the context, rules out treatable causes and designs the plan with you, in private and without rushing, working with pelvic physiotherapy, sex therapy or other specialties when needed.

  • Physical examination and medical historyA conversation about what has changed, review of medication and clinical history, gynaecological examination when indicated and a questionnaire on sexual function.
  • A plan tailored to youFirst treating the contributing factors and the first-line options; additional treatments only if appropriate, with the evidence explained.
  • No obligationThe cost of any treatment is confirmed only after the assessment.
Book an assessment consultation

Book a consultation

Book your consultation

Choose how you prefer to get in touch. We will arrange the assessment consultation with Dr Michelle Campagnoli.

Booking through the website100€70€Assessment consultationExclusive price for those who book the assessment through the website. Outside the website, the price is 100 €.

New Life Miraflores, Algés · Office Center, R. Santa Teresa do Menino Jesus n.º 6, 9.º C, 1495-048

Your details are used only for this contact. Any treatment depends on a prior medical assessment.

Request an appointmentIt takes less than a minute.
Speciality
You do not need to go into detail. The doctor will talk to you during the consultation.
Request received. Our team will contact you as soon as possible.
Why are my orgasms less intense?

There is almost never a single cause. The most frequent are the hormonal changes of perimenopause and the menopause, which thin the mucosa and can bring dryness and less desire, the state of the pelvic floor, medications such as some antidepressants, stress, tiredness and the quality of the relationship, and also illnesses or surgeries. Only an assessment shows what is contributing in your case.

Is it normal for orgasms to change with age?

It is common for sexual response to change over a lifetime, and orgasm may become weaker, shorter or need more stimulation. This does not mean nothing can be done. If the change bothers you, it deserves assessment, because some causes, such as dryness, medication or pain, have treatment.

Is having less intense orgasms the same as not being able to have an orgasm?

No. Here the orgasm happens, but it is weaker or less satisfying. Not being able to reach orgasm, or taking a very long time to get there, are other situations, with approaches that partly overlap but are assessed separately.

Can antidepressants make orgasm less intense?

They can. Some antidepressants, especially those that act on serotonin, are associated with orgasm problems, and in a meta-analysis sexual dysfunction ranged from about 26% to 80% depending on the drug, with some having an effect comparable to placebo. Do not stop or change the dose on your own: talk to the doctor who prescribes it, who can consider an adjustment or an alternative.

Do pelvic floor exercises help?

They can help some women. A meta-analysis in postmenopausal women found improvement in the orgasm domain, but with very different results between trials, and an observational study linked a stronger pelvic floor to better orgasmic response. It is worth having a professional first assess whether what is lacking is strength or relaxation, because the exercises do not suit everyone.

Does sex therapy work?

For many women, an important part of the cause is psychological and relational, and sex therapy, individual or as a couple, and mindfulness approaches can help. It is one of the lines of treatment considered for orgasm problems, and does not rule out also treating a physical cause.

Do hormones, oestrogen or testosterone help?

Low-dose vaginal oestrogen, prescribed by a doctor, treats the dryness and atrophy of the menopause and, by making sex more comfortable, may help indirectly. If you have or have had breast cancer, speak to your oncologist first. Testosterone is not a treatment for orgasm: the international consensus only recognises it in postmenopausal women with low sexual desire that causes them distress, and always with medical follow-up.

Does the O-SHOT (PRP) improve orgasm?

There is no solid evidence. A 2023 systematic review considered the level of evidence low, and a 2026 pilot trial of 52 premenopausal women found improvement in the total sexual score at 6 weeks, but the specific improvement in orgasm was no different from that of the control group. It is an additional option, assessed case by case, after the most common causes have been treated, and not a promise.

What about vaginal laser or radiofrequency for orgasm?

We do not propose them for this problem. In 2018 the FDA warned that it has not approved energy devices to treat menopausal symptoms, urinary incontinence or sexual function, and that they can cause burns, scarring, pain during sex and chronic pain. The evidence for sexual function is insufficient, and the decision is always explained and shared with you.

When should I book a consultation?

Book a consultation if the change bothers you, if it appeared after a medication, a birth or surgery, or if it comes with dryness, pain, less desire or sadness. If you have bleeding after the menopause or after sex, abnormal discharge, persistent pain or a changing lesion on the vulva, book early, or call SNS 24 (808 24 24 24) out of hours. If you have suddenly lost sensation in the intimate area or in the legs, with loss of control of urine or stools, call 112.

We could not find that question. Ask us on WhatsApp

Scientific references

This page is based on the sources below and was reviewed by Dr. Michelle Campagnoli. Last updated on .

  1. Laan E, Rellini AH, Barnes T; International Society for Sexual Medicine. Standard operating procedures for female orgasmic disorder: consensus of the International Society for Sexual Medicine. Journal of Sexual Medicine 10(1):74-82, 2013.
  2. Meston CM, Levin RJ, Sipski ML, Hull EM, Heiman JR. Women's orgasm. Annual Review of Sex Research 15:173-257, 2004.
  3. Serretti A, Chiesa A. Treatment-emergent sexual dysfunction related to antidepressants: a meta-analysis. Journal of Clinical Psychopharmacology 29(3):259-266, 2009.
  4. Lowenstein L, Gruenwald I, Gartman I, Vardi Y. Can stronger pelvic muscle floor improve sexual function?. International Urogynecology Journal 21(5):553-556, 2010.
  5. García-Laria R, Alonso-Calvete A, Justo-Cousiño L, Da Cuña-Carrera I, Soto-González M. Effects of pelvic floor muscle training on sexual function of postmenopausal women. A systematic review and meta-analysis. Sexual Medicine 13(4):qfaf067, 2025.
  6. Clarke B, Gaddam N, Garcia B, Iglesia CB, Podolsky R, Dieter AA. Vaginal injection of platelet-rich plasma for sexual function: a randomized controlled trial. Obstetrics & Gynecology 147(5):627-635, 2026.
  7. Dankova I, Pyrgidis N, Tishukov M, et al. Efficacy and safety of platelet-rich plasma injections for the treatment of female sexual dysfunction and stress urinary incontinence: a systematic review. Biomedicines 11(11):2919, 2023.
  8. The NAMS 2020 GSM Position Statement Editorial Panel. The 2020 genitourinary syndrome of menopause position statement of The North American Menopause Society. Menopause 27(9):976-992, 2020.
  9. Medsafe (Nova Zelândia), a retransmitir o alerta da U.S. FDA. Safety Information: energy-based devices used for vaginal 'rejuvenation' or vaginal cosmetic procedures (relays the USFDA safety communication of July 2018). Medsafe, New Zealand Medicines and Medical Devices Safety Authority, 2018.
  10. Davis SR, Baber R, Panay N, et al. Global consensus position statement on the use of testosterone therapy for women. Journal of Clinical Endocrinology & Metabolism 104(10):4660-4666, 2019.
  11. NHS. Symptoms of menopause and perimenopause. (NHS website, acedido 2026-11-11)
CallAssistantAvailableBook


